Who this is for
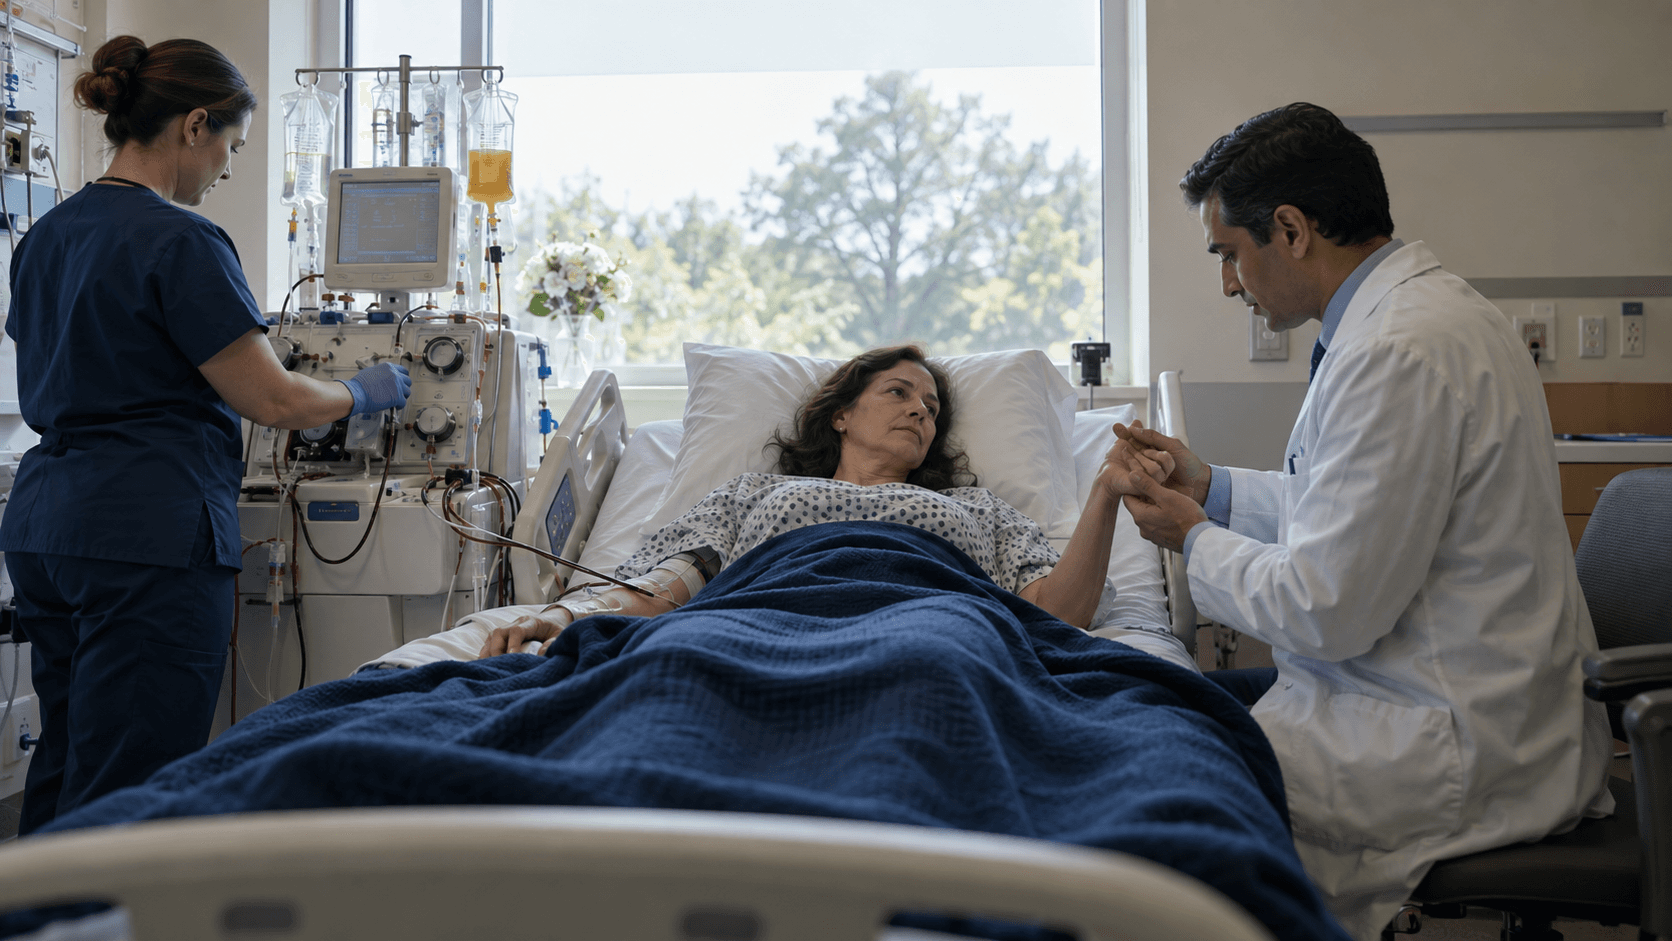
Therapeutic plasma exchange (TPE) is used in selected neurologic autoimmune diseases when a neurologist judges that removing circulating antibodies or other plasma factors will change the acute course. It is hospital or apheresis-unit care, not a wellness visit. The American Academy of Neurology (AAN) has published guidance on plasma exchange (often called plasmapheresis in those papers) for Guillain-Barré syndrome (GBS) and a broader assessment of neurologic indications. The American Society for Apheresis (ASFA) assigns categories to specific myasthenia gravis (MG), GBS, chronic inflammatory demyelinating polyneuropathy (CIDP), and other fact sheets.
Typical candidates are people with severe GBS who cannot walk, MG crisis or impending crisis with bulbar or respiratory risk, short-term CIDP management in selected patients, and a few other antibody-mediated syndromes a neuromuscular or neuroimmunology team names. People with stable, treated MG, nonspecific fatigue, or “autoimmune aging” are not automatic TPE candidates.
This page is for patients who have been offered TPE by neurology, or who saw TPE advertised next to peptides and IVs. Licensed neurologists, intensivists, and apheresis physicians own the indication. Trained apheresis staff run the circuit. Longevity TPE for aging remains speculative, costly, and not a proven substitute for disease-modifying neurologic care.
- Often considered: severe GBS; selected MG crisis; short-term CIDP in AAN/ASFA contexts.
- Not offered (AAN): chronic or secondary progressive multiple sclerosis.
- Not an indication: wellness, brain fog without a diagnosis, or preventive longevity.
What options clinics actually offer
Hospital and academic neurology services offer TPE as a time-limited series, commonly 1 to 1.5 plasma volumes per session for several days, usually with 5% albumin. Vascular access may be peripheral large-bore needles or a central catheter. Citrate anticoagulation, calcium monitoring, and after-hours coverage for hypotension, circuit clotting, and line infection are part of a real program.
Intravenous immunoglobulin (IVIG) is an alternative for many GBS patients; AAN treats PE and IVIG as similarly effective in key GBS groups and does not recommend stacking them as a routine sequence. MG teams may choose TPE when they need a rapid effect, when IVIG is unsuitable, or perioperatively. That choice is neurology-directed. A cash-pay clinic that only offers TPE because it owns a centrifuge is not equivalent.
ASFA’s ninth special issue is the current North American catalog of graded apheresis indications. Wellness longevity does not appear as a Category I neurologic indication. If a clinic cannot say whether your case is GBS, MG crisis, CIDP, or something else, and cannot name the covering neurologist, you are not in a standard neurologic TPE pathway.
What evidence supports
AAN GBS immunotherapy guidance, reaffirmed in recent years, recommends plasma exchange for nonambulant adults within four weeks of neuropathic symptom onset and considers it for ambulant patients seen early. IVIG is an equivalent option in overlapping windows. Steroids alone are not GBS treatment. Sequential PE then IVIG is not recommended as a default.
The 2011 AAN plasmapheresis guideline (PMC) found plasma exchange established as effective for severe acute inflammatory demyelinating polyneuropathy/GBS and for short-term CIDP (Level A). It found plasma exchange ineffective for chronic or secondary progressive MS (Level A, should not be offered). For MG, that AAN assessment judged randomized evidence insufficient (Level U), even though TPE is widely used in crisis and ASFA categorizes selected MG indications as first-line. That gap is why you want a neurologist, not a blog, to weigh TPE against IVIG and other MG therapies.
ICU apheresis reviews catalog harms that apply in neurology units too: citrate hypocalcemia, catheter infection and thrombosis, hypotension, and allergic reactions if plasma is used. Those risks are accepted when the alternative is ventilation or lasting disability. They are not a reasonable trade for an unproven aging protocol. Animal dilution studies do not rewrite AAN MS conclusions or create a new MG indication called longevity.
When to see a clinician first
Seek emergency care for rapidly rising weakness, trouble swallowing or breathing, double vision with bulbar symptoms, or suspected GBS after an infection. Do not wait for an elective TPE booking. Airway management outranks the machine.
See neurology before any cash-pay exchange if you have MG, CIDP, MS, or unexplained neuropathy. Ask whether the indication is ASFA Category I or II, whether IVIG is equivalent, and how many sessions they plan. If the clinic offers TPE for “neuroinflammation” without an exam, EMG, antibody testing, or imaging as indicated, that is marketing.
People with active infection, severe hypocalcemia, uncontrolled arrhythmia, or no usable access need a hospital plan. Pregnancy, anticoagulation, and immunoglobulin A deficiency change risk. AAN’s negative MS finding matters: progressive MS is not a reason to start TPE because a longevity clinic has a chair open.
How to judge progress
Use the deficit the neurologist named. In GBS, that is walking, ventilation days, and strength over weeks—not same-day energy. In MG, it is swallowing, vital capacity, diplopia, and crisis avoidance. In CIDP, it is a defined disability score over a planned course. If nothing changes, neurology reassesses the diagnosis; you do not automatically buy more elective TPE.
Watch the line. Fever, pus, arm swelling, or shortness of breath after catheter placement is an infection or clot until proven otherwise. Perioral tingling during the run is often citrate-related hypocalcemia and should be treated, not reframed as detox. Keep scheduled MG or CIDP medicines unless the neurologist changes them. TPE removes antibodies and also some drugs.
Do not judge neurologic TPE by epigenetic clocks or a “plasma age.” Those metrics are not AAN endpoints. When the series ends, the success question is whether the named autoimmune attack eased enough to support rehab, ventilation weaning, or a longer-term immunotherapy plan. Wellness TPE that never named a disease cannot be scored that way—and should not replace neurology.
Frequently Asked Questions
References
AAN: Immunotherapy for Guillain-Barré syndrome (practice guideline)
https://www.aan.com/Guidelines/home/GuidelineDetail/59PMC: AAN evidence-based guideline update on plasmapheresis in neurologic disorders
https://pmc.ncbi.nlm.nih.gov/articles/PMC3034395/ASFA: JCA Special Issue 9th Edition (therapeutic apheresis guidelines)
https://www.apheresis.org/news/647089/JCA-Special-Issue-9th-Edition-Now-Available.htmASFA: Guidelines page
https://www.apheresis.org/page/GuidelinesPMC: Plasma exchange in the intensive care unit
https://pmc.ncbi.nlm.nih.gov/articles/PMC9372988/NHLBI: Thrombotic Thrombocytopenic Purpura (TTP)
https://www.nhlbi.nih.gov/health/thrombotic-thrombocytopenic-purpura Your Privacy Choices