What you are comparing
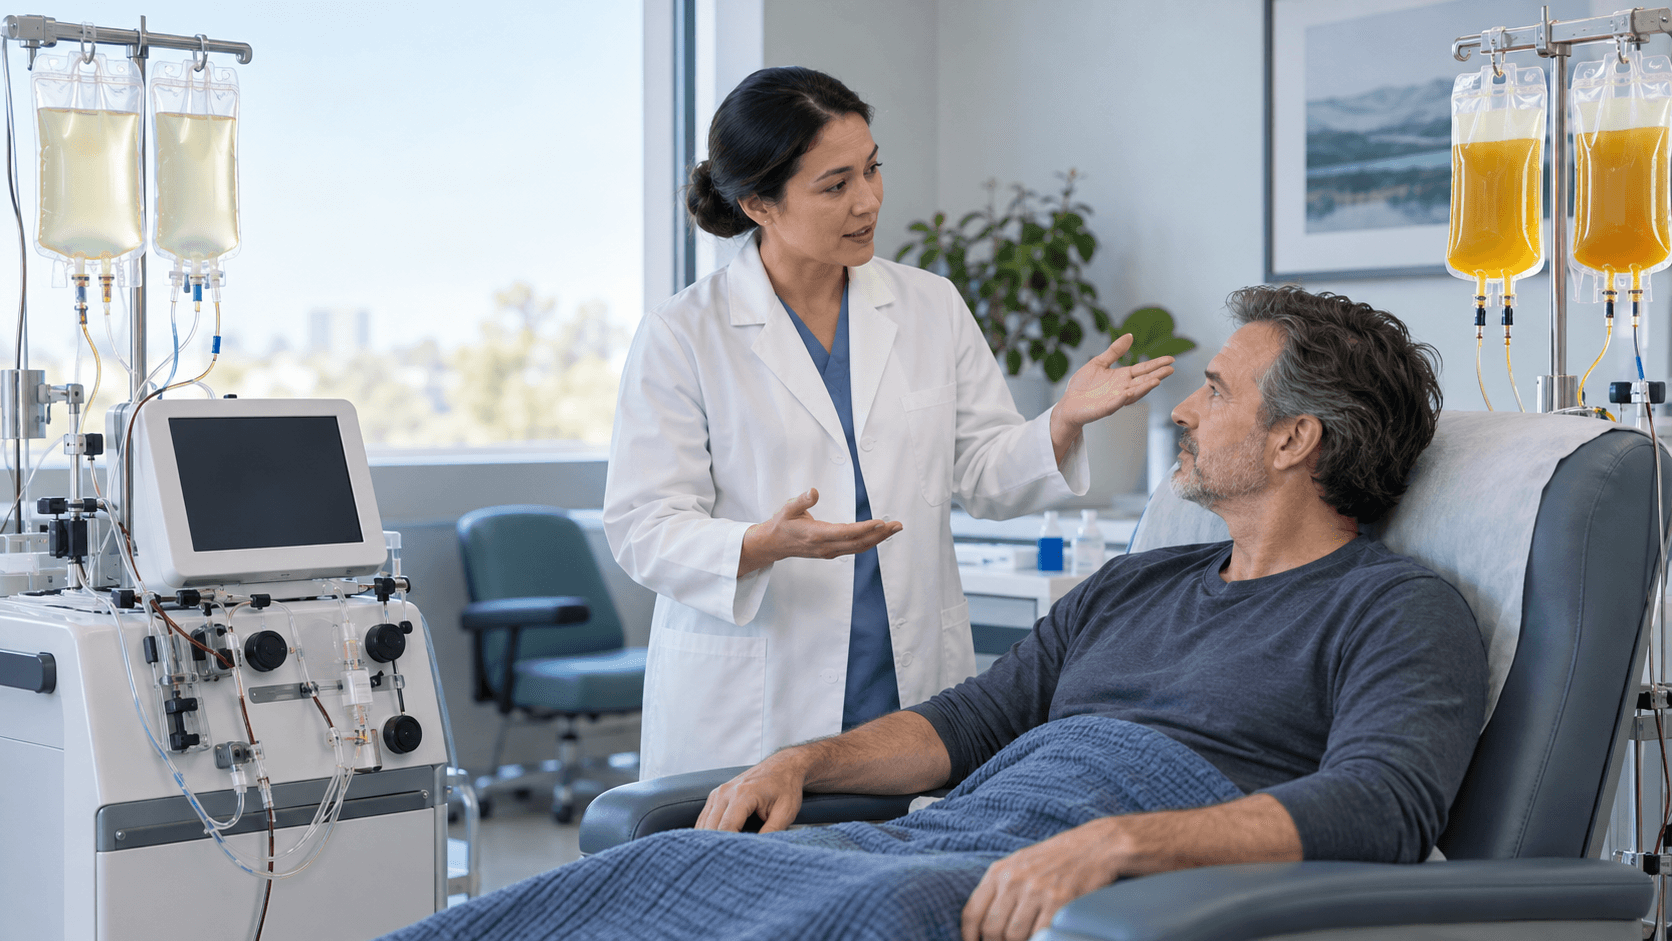
During therapeutic plasma exchange (TPE), a machine separates plasma from blood cells. The plasma is discarded. Something must go back in so blood volume and oncotic pressure do not collapse. The two standard replacement fluids are 5% human albumin (sometimes mixed with saline) and donor plasma, often called fresh frozen plasma or a related plasma product.
This is not a branding choice. The American Society for Apheresis (ASFA) frames TPE as a procedure with a named disease, a category, and a replacement strategy. NHLBI describes acquired TTP treatment as replacement with donor plasma. Hyperviscosity reviews typically describe albumin. Intensive-care reviews state plasma is indicated when the goal is to replace plasma components such as ADAMTS13, while albumin is used when the goal is removal.
Longevity clinics sometimes advertise “plasma exchange with albumin” as a gentler, blood-product-free reset. That sentence can be technically true for an elective dilution and still be the wrong fluid for TTP. Conversely, infusing large volumes of plasma into a person who needed albumin adds transfusion reactions without treating an enzyme deficiency. The comparison is indication-specific, not a contest of which bag looks more medical.
FDA regulates plasma components and has labeled certain pathogen-reduced plasma products for transfusion or TPE in TTP. Albumin is a licensed biologic with separate labeling. Neither product is a proven aging drug. TPE remains a hospital or specialty procedure with infection, clotting, hypocalcemia, and access complications regardless of which fluid is chosen.
How they differ
Albumin restores volume and protein oncotic pressure. It does not restore clotting factors, ADAMTS13, or immunoglobulins. After large albumin exchanges, fibrinogen and other factors fall until the liver replaces them. That may be acceptable when bleeding risk is low and the target is an autoantibody or paraprotein. It is unacceptable as sole replacement in acquired TTP, where missing ADAMTS13 is the disease.
Donor plasma contains ADAMTS13, coagulation proteins, and other plasma constituents. It is the default for TTP. It also contains citrate and donor proteins, so allergic reactions, transfusion-related acute lung injury, and infectious-disease residual risk are higher than with albumin. ICU reviews list plasma replacement and citrate as risk factors for hypocalcemia and paresthesia. Plasma is a scarce, screened blood product, not a wellness ingredient.
Some TTP services use a 50/50 albumin-then-plasma sequence to cut plasma exposure while still infusing enzyme. That is a hematology protocol with published observational data, not evidence that albumin-only TPE treats TTP. Hyperviscosity from IgM usually needs albumin because the job is to remove a thick protein, not to donate clotting factors the patient did not lack.
- Albumin: removal-focused exchanges; no ADAMTS13; lower allergic load; factor depletion.
- Plasma: TTP and selected factor-replacement settings; higher reaction and citrate load.
- Mixtures: protocol-specific, usually under a transfusion-medicine order, not a menu upgrade.
- Either: needs access, anticoagulation, and a covering clinician for line infection and clotting.
Who each option is for
Donor plasma is for people with a disease that requires replacement of a plasma protein—acquired TTP being the textbook case. NHLBI and FDA adjunct-drug labeling both assume plasma exchange, not albumin-only dilution. People with active TTP belong in a hospital, not a membership suite.
Albumin is for many ASFA-listed removal indications when clotting-factor replacement is not the goal: symptomatic hyperviscosity, selected neurologic autoimmune exchanges, and other settings an apheresis physician names. It is a poor solo plan for TTP, for someone about to have a high-bleeding-risk procedure without a factor plan, or for anyone whose only “indication” is aging.
Well adults seeking longevity TPE are not an ASFA indication for either fluid. If they still pursue elective exchange in a research or cash-pay setting, albumin is typically used because there is no ADAMTS13 to replace—but that does not make the procedure proven, inexpensive, or risk-free. People with IgA deficiency, prior plasma anaphylaxis, or unstable volume status need an individualized hospital plan, not a standing order from a salesperson.
Risks of choosing the wrong one
Choosing albumin for TTP fails to replete ADAMTS13 and can worsen a depletion coagulopathy on top of thrombocytopenia. That is a preventable hemorrhage and organ-failure pathway. Choosing plasma for a straightforward albumin indication adds allergic reactions, extra citrate hypocalcemia, and unnecessary donor exposure. Neither error is a wellness preference.
Access complications do not care which bag is hanging. Central lines clot and infect. Peripheral large-bore needles infiltrate. Circuit clotting aborts the run. Citrate chelates calcium with both fluids; plasma often adds more citrate. Tingling around the mouth, tetany, or QT changes are medical events, not a “detox” feeling.
Marketing that calls albumin TPE “the same as TTP treatment, just preventive” is false. Marketing that calls plasma TPE “young blood” is also false: donor plasma is matched and screened for transfusion, not selected as a youth elixir. FDA does not license either product as an anti-aging therapy.
How to decide
Start with the diagnosis. If TTP is on the table, the fluid is plasma (or a defined plasma-containing protocol) in a hospital that can exchange the same day. If the problem is symptomatic hyperviscosity, albumin plus clone-directed therapy is the usual pair. If there is no ASFA-aligned disease, the honest decision may be not to exchange at all.
Ask the apheresis physician which product, what volume (often 1 to 1.5 plasma volumes), and why. Ask how they monitor ionized calcium, fibrinogen, and blood pressure. Ask who is on call for anaphylaxis, TRALI, line sepsis, and circuit clotting. ASFA patient sheets exist because this is a procedure with terminology, not a spa add-on.
Do not let cost alone pick the bag. Plasma is more expensive and more reactogenic; albumin is not “safer TTP care.” For elective longevity claims, price the lack of proven aging benefit and the real harms—infection, clotting, hypocalcemia, access injury—before you compare SKUs. Keep hematology in charge when TTP or a paraprotein is involved. A wrong fluid is not a small substitution. It is a different treatment.
Frequently Asked Questions
References
NHLBI: Thrombotic Thrombocytopenic Purpura (TTP)
https://www.nhlbi.nih.gov/health/thrombotic-thrombocytopenic-purpuraFDA: INTERCEPT Blood System for Plasma, including TPE in TTP
https://www.fda.gov/vaccines-blood-biologics/approved-blood-products/intercept-blood-system-plasmaASFA: JCA Special Issue 9th Edition (therapeutic apheresis guidelines)
https://www.apheresis.org/news/647089/JCA-Special-Issue-9th-Edition-Now-Available.htmASFA: Patient resource information sheets, including plasma exchange
https://www.apheresis.org/page/FactSheetsPMC: Plasma exchange in the intensive care unit
https://pmc.ncbi.nlm.nih.gov/articles/PMC9372988/PMC: Hyperviscosity syndrome in paraprotein-secreting conditions
 Your Privacy Choices