What this means
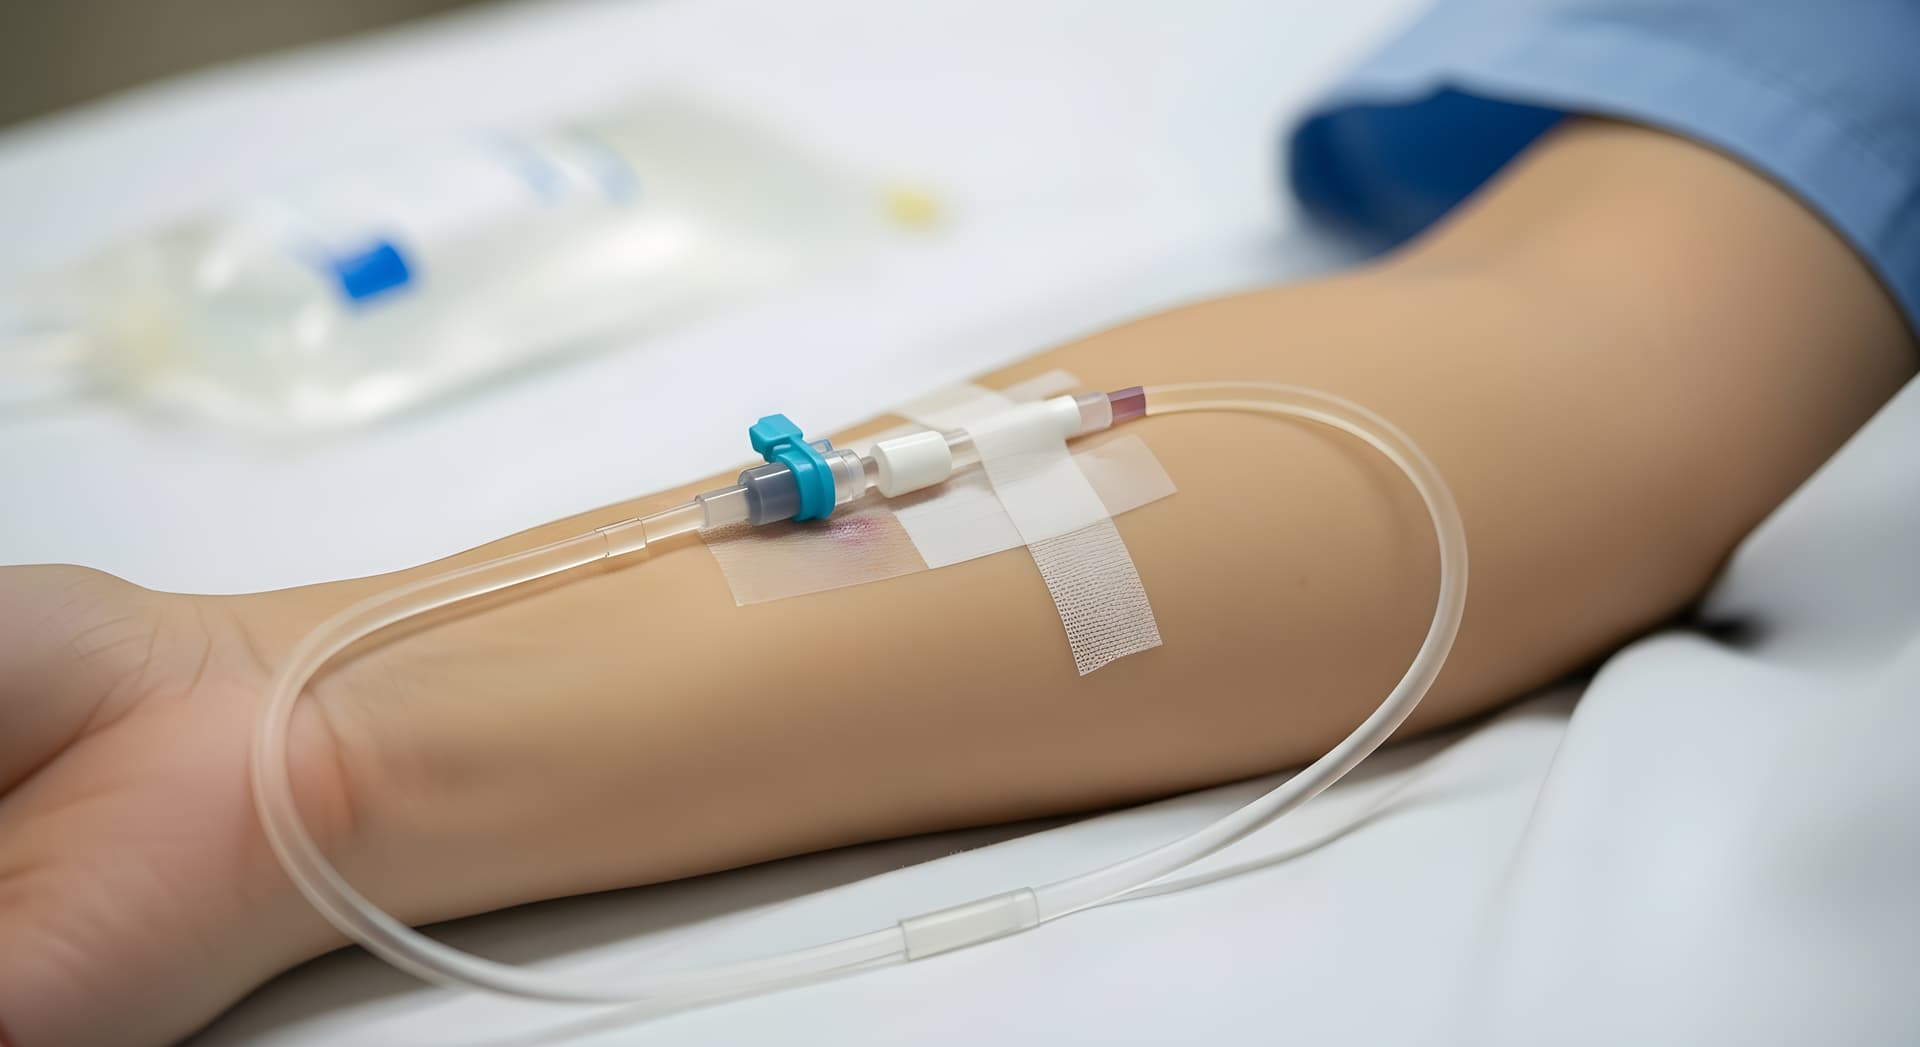
Chelating agents are drugs, not wellness ingredients. A chelator binds a metal ion so the kidneys or other routes can excrete it. In U.S. medical practice that means a labeled prescription medicine used for a documented poisoning or a related specialist indication—selected lead poisoning after exposure is stopped, or iron overload under hematology care. The agent, the metal, the route, and the monitoring plan are not interchangeable products on a longevity menu.
EDTA, succimer (DMSA), dimercaprol, and DMPS are different molecules. Calcium disodium EDTA is used in defined lead-poisoning settings. Disodium EDTA is a different salt that can drop blood calcium and has caused fatal medication errors. Succimer is an oral chelator used in selected pediatric lead cases. DMPS appears in some compounding and overseas protocols; it is not a casual detox drop. The Agency for Toxic Substances and Disease Registry and the Centers for Disease Control and Prevention treat these as specialist drugs.
The Food and Drug Administration has warned that over-the-counter sprays, drops, baths, and supplements marketed as chelation to treat disease are unapproved. The agency has also flagged home urine metal tests used to justify those products. A clinic that sells “EDTA for toxins” without a validated blood or urine level is not practicing toxicology. Fatigue, brain fog, or a cash-pay panel is not a labeled indication.
What the evidence shows
Medical chelation has a narrow sequence: stop the exposure, confirm the metal with a validated test, then treat when criteria are met. CDC childhood lead guidance reserves chelation discussion for very high confirmed venous blood lead levels, typically with a medical toxicologist or experienced pediatrician. ATSDR medical management pages state chelation should never be given prophylactically or during ongoing lead exposure. Those rules are the opposite of a standing wellness drip.
Chelators have real toxicities. They can deplete essential minerals, injure kidneys, cause neutropenia with succimer, and, when the wrong EDTA salt is used, precipitate life-threatening hypocalcemia. A PubMed Central review of clinical chelation describes monitoring of kidney function and minerals as routine, not optional. MedlinePlus notes that chelation can have serious side effects and is a risk-benefit decision after a documented metal problem—not after a marketing brochure.
There is no credible evidence that serial chelation extends lifespan, reverses atherosclerosis as a lifestyle product, or treats autism, fatigue, or unnamed “body burden.” FDA’s consumer Q&A specifically called out marketing for heart disease, autism, and other unrelated conditions. A research trial of EDTA in selected coronary disease is not a license for cash-pay detox series. If a clinician cannot name the metal, the lab method, and the stop rule, you are not in that research setting.
- Indicated: documented poisoning or selected iron-overload care, with exposure stopped and labs scheduled.
- Not indicated: fatigue, wellness, autism, or heart disease sold as detox.
- Wrong salt: disodium EDTA is not a substitute for calcium disodium EDTA.
Common myths
Myth: everyone has toxic metals that need to be “pulled.” Modern laboratories can measure trace metals in healthy people. A number on a printout is not a diagnosis. ATSDR and CDC start with a credible exposure history and a test matched to the specific metal. Background detection does not authorize a drug that can injure kidneys.
Myth: a provoked urine test after a chelator proves you need treatment. Giving a chelator and then measuring urine metals will often raise excretion. That does not prove you were poisoned. FDA warned that some companies use urine screening to sell unapproved products. ATSDR Case Studies in Environmental Medicine and CDC authors have advised against provoked testing because reference ranges do not apply and the drug itself can harm.
Myth: natural or over-the-counter chelators are safer. FDA has never approved an OTC chelation product for any health condition. Clay baths, nasal sprays, and EDTA suppositories sold to treat disease are unapproved drugs in that framing, not gentler versions of hospital care. Myth: chelation is a longevity protocol. Removing a documented poison can be lifesaving. Removing normal background metals is not an aging treatment. Your liver and kidneys already handle everyday clearance.
How clinics use it
Responsible use is uncommon on longevity menus. A physician or medical toxicologist who suspects lead, mercury, or another metal orders a standard, unprovoked test, works to remove the source, and refers to poison control or a Pediatric Environmental Health Specialty Unit when levels are high. If a labeled chelator is used, the clinician names the drug, the salt, the indication, and the laboratory schedule. Children and pregnant people go through pediatric or obstetric pathways, not a spa protocol.
Cash-pay clinics often invert that sequence. They sell a urine panel, declare a burden, and book a series of EDTA or DMPS infusions. Some add glutathione or sauna and call the stack a protocol. That pattern matches the FDA warning more than ATSDR care. Ask who holds a state medical license, which clinical laboratory performs the assay, and what happens if the result is normal. If the answer is that you still need a series, you are in a sales funnel.
Infusion harms are independent of the metal story: infection from compounding, allergic reaction, and fluid or electrolyte shifts. Pairing a chelator with heat or aggressive fluids can add dehydration. A clinic that will not share an adverse-event plan, the compounding source, or a stop rule is not a safe default. Licensed decisions stay with licensed clinicians.
Practical takeaway
Treat chelators as prescription drugs for documented poisoning. If you have a plausible exposure—pre-1978 paint, occupational dust, imported products, or well water—see a physician and ask for a validated test matched to that metal. Do not start over-the-counter chelators. Do not accept a provoked urine graph as a diagnosis. Keep ordinary care in place while you sort the exposure question: anemia, thyroid disease, depression, and sleep apnea can look like “toxins.”
- Name the exposure and the metal before anyone names a drip.
- Refuse OTC chelation kits and urine tests used only to sell treatment.
- If a prescription chelator is truly indicated, ask about kidney monitoring and essential-mineral replacement.
- Call poison control or emergency services for confusion, seizure, or known high-dose ingestion.
A trustworthy clinician can explain why they are not chelating you. Silence, guaranteed clearance, or a standing EDTA protocol for everyone is your cue to leave. Licensed toxicology is narrow and monitored. Wellness chelation is a red flag, not a longevity tool.
Frequently Asked Questions
References
FDA: Questions and Answers on Unapproved Chelation Products
https://www.fda.gov/drugs/medication-health-fraud/questions-and-answers-unapproved-chelation-productsCDC: Recommended Actions Based on Blood Lead Level
https://www.cdc.gov/lead-prevention/hcp/clinical-guidance/index.htmlATSDR: Lead Toxicity — Patient Treatment and Management
https://archive.cdc.gov/www_atsdr_cdc_gov/csem/leadtoxicity/patient_treatment.htmlATSDR: Lead Medical Management Guidelines
https://wwwn.cdc.gov/tsp/MMG/MMGDetails.aspx?mmgid=1203&toxid=22MedlinePlus: Heavy Metal Blood Test
https://medlineplus.gov/lab-tests/heavy-metal-blood-test/PMC: Chelation in Metal Intoxication
 Your Privacy Choices