Overview
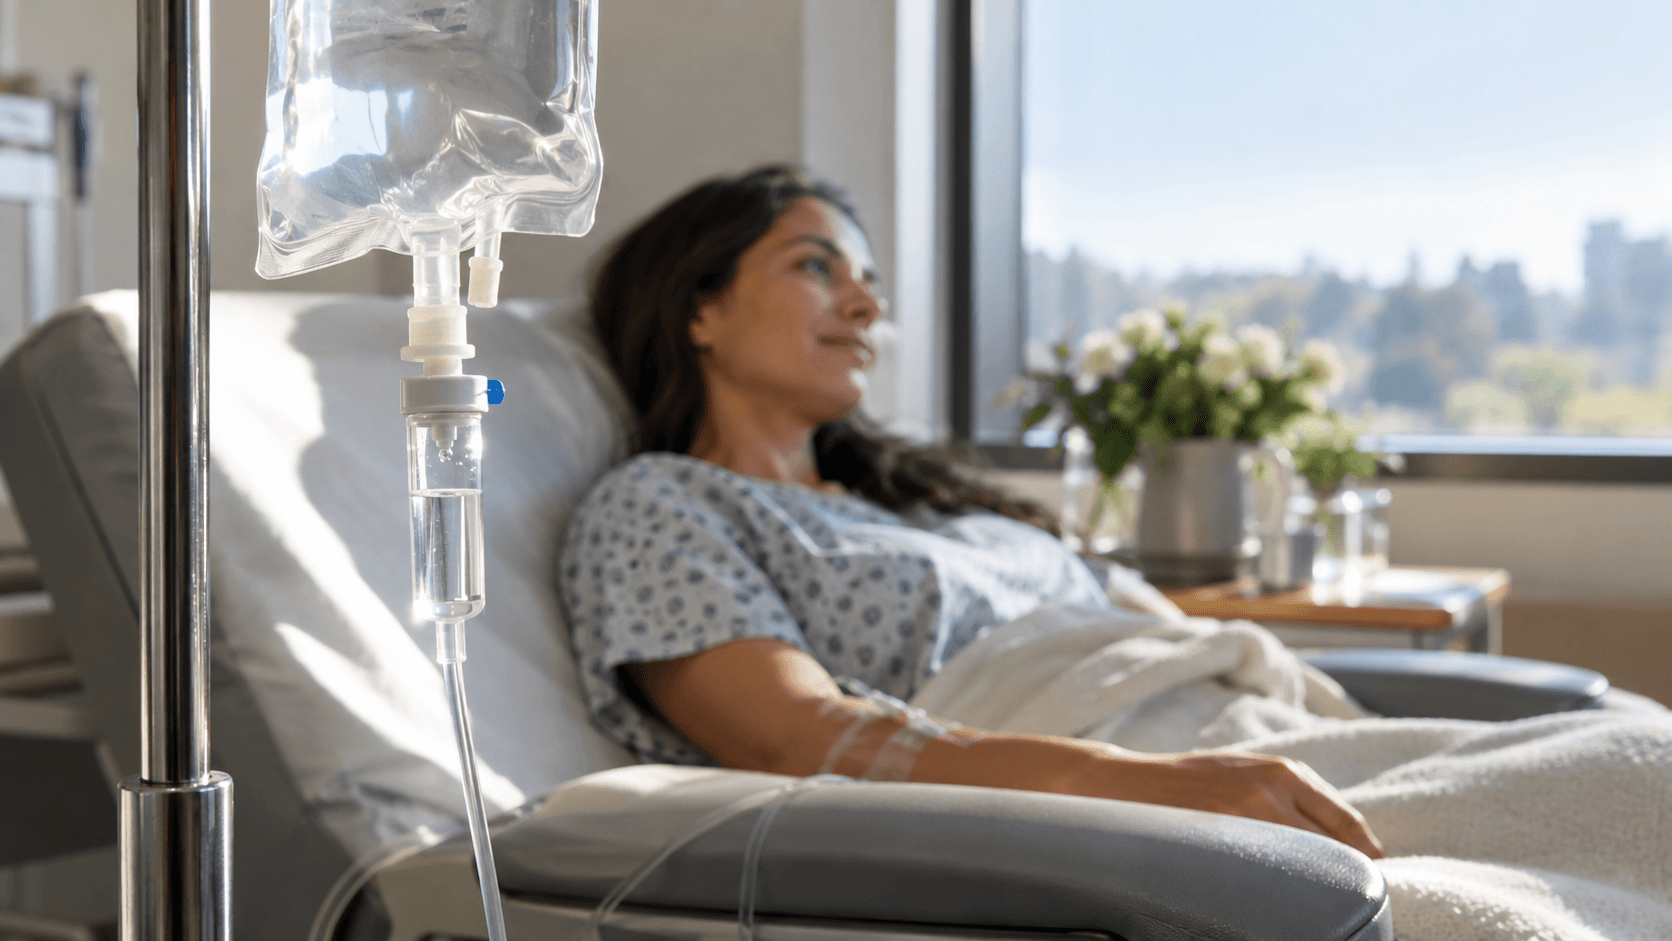
Hydration IV Therapy delivers sterile isotonic fluid directly into a vein to expand plasma volume and replace water and electrolytes lost through sweating, gastrointestinal illness, heat, alcohol, or inadequate oral intake. In longevity and wellness clinics it is the most common IV service: a 500–1,000 mL bag of normal saline or a balanced crystalloid such as lactated Ringer’s, with optional potassium, magnesium, or a light micronutrient add-on.
What It Includes
Isotonic crystalloids: 0.9% sodium chloride (normal saline) or balanced solutions (lactated Ringer’s, Plasma-Lyte) that more closely match plasma electrolyte composition.
Electrolytes: sodium is inherent to the bag; potassium, magnesium, or calcium may be added when labs or symptoms suggest a deficit—and only after screening for renal function.
Optional add-ons: B vitamins or vitamin C are sometimes combined in “hydration plus” drips; these change the visit from volume replacement into a nutrient infusion and should be disclosed on the label.
Mechanisms
Oral fluids must be absorbed across the gut and are limited by gastric emptying, nausea, and ongoing losses. IV crystalloids bypass that bottleneck and raise intravascular volume within minutes, supporting blood pressure, tissue perfusion, and renal clearance. Balanced solutions reduce the hyperchloremic acid load of large-volume saline. Electrolyte additives restore transmembrane gradients that affect muscle, nerve, and cardiac function. This is physiology of volume replacement—not a detox, immune reset, or hangover cure in the pharmacologic sense.
Evidence & Limits
Intravenous fluids are standard of care for clinically significant dehydration, hypovolemia, and peri-procedure NPO states. Sports-medicine guidance still prefers oral rehydration for most athletes when the gut is functional. Elective hangover, jet-lag, and “wellness hydration” drips are widely offered; randomized outcome data for those marketing claims are sparse. Position hydration IV as rapid volume support when oral intake is limited or losses are high—not as a weekly lifestyle requirement for otherwise hydrated adults.
Safety
The main risks are fluid overload (heart failure, kidney disease, poorly controlled hypertension), electrolyte shifts, vein irritation, and infection from breaks in sterile technique. Screen cardiac and renal history, current diuretics or SGLT2 inhibitors, and pregnancy. Use USP-compliant sterile products and aseptic IV placement. Stop or slow the infusion for chest tightness, dyspnea, or a rising blood pressure.
Summary
Hydration IV Therapy is targeted volume replacement. It is most useful after true fluid losses or when drinking is not practical, and least useful as a stand-in for daily water, electrolytes from food, and recovery sleep.
Benefits
Rapid plasma-volume restoration when oral intake is limited
Predictable delivery of sodium and, when added, potassium or magnesium
Useful around travel, heat, GI losses, procedures, or hard training blocks
Short outpatient visit with little or no downtime
Can be combined with micronutrients when a clinician has a specific goal
The Procedure
1
Intake & Screening
2
Formula Selection
3
IV Placement
4
Infusion
5
Completion & Aftercare
Preparation
Eat a light meal if you tolerate food; continue oral fluids unless a clinician has restricted them. Wear a sleeve that rolls above the elbow. Bring a medication list, including diuretics, blood-pressure drugs, and supplements. Tell staff about heart, kidney, or blood-pressure conditions.
Recovery & Aftercare
Most people return to normal activity immediately. Increased urination is expected. Mild coolness at the IV site or transient lightheadedness can occur. Continue drinking water and electrolyte-containing foods unless advised otherwise.
Risks & Considerations
Fluid overload (shortness of breath, swelling, rising blood pressure)—higher risk with heart or kidney disease; vein irritation, bruising, infiltration; infection from poor sterile technique; electrolyte imbalance if additives are used without screening; rare hypersensitivity to bag components. Hydration IV is not appropriate as a substitute for emergency care of severe dehydration, heat stroke, or alcohol poisoning.
Frequently Asked Questions
References
[1]
World Health Organization. Intravenous Fluids: Clinical Principles (2023).
https://www.who.int/publications/i/item/9789240064157[2]
Semler M.W. et al. Balanced Crystalloids versus Saline in Critically Ill Adults (N Engl J Med, 2018).
https://doi.org/10.1056/NEJMoa1711584[3]
National Institute for Health and Care Excellence. Intravenous Fluid Therapy in Adults in Hospital (CG174).
https://www.nice.org.uk/guidance/cg174[4]
Sawka M.N. et al. ACSM Position Stand: Exercise and Fluid Replacement (Med Sci Sports Exerc, 2007).
https://doi.org/10.1249/mss.0b013e31802ca597[5]
CDC. Injection Safety and Safe Practices (One & Only Campaign).
https://www.cdc.gov/injection-safety/[6]
USP <797> Sterile Compounding Standards (overview).
https://www.usp.org/compounding/usp-compounding-standards Your Privacy Choices